
This case was originally published in 2018. The information provided in this case was accurate and correct at the time of initial program release. Any changes in terminology since the time of initial publication may not be reflected in this case.
Clinical History
A 55-year-old woman presented with dizziness. MRI showed a 2.5 x 1.5 x 1.7 cm suprasellar mass with associated hemorrhage, expansion of the sella, and superior displacement of the optic chiasm (Image A). The patient denied visual disturbances but admitted to intermittent headaches. There were no clinical signs or symptoms of pituitary dysfunction. All lab results were normal including a 24-hour urine cortisol and the lesion was thought to be a nonfunctioning macroadenoma of the pituitary. An endonasal transsphenoidal resection was performed.
Tissue Site
Pituitary/suprasellar region
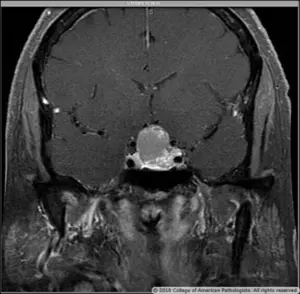
Image A: Presurgical MRI, coronal T1-weighted, post-gadolinium. |
Whole Slide Image
The whole slide image provided is a Periodic Acid Schiff stained slide of Suprasellar mass from an Endonasal transsphenoidal resection.
Questions
- What is the MOST likely diagnosis?
- Aneurysm
- Craniopharyngioma
- Crooke cell adenoma
- Mucormycosis
- Pituitary apoplexy
- What is the microscopic feature identified by arrows in this image?
- Apoptotic bodies
- Crooke hyaline change
- Early necrotic change
- Fungal organisms
- Viral inclusions
- It is important to identify this lesion because of which of the following?
- The radiographic appearance shows infiltration within cortex.
- This is a slow growing tumor and responds well to radiation therapy.
- This lesion is almost always endocrinologically silent.
- This lesion is indolent and does not require treatment.
- This lesion is invasive and often has an aggressive course.
Discussion and Diagnosis
The diagnosis for this case is Crooke cell adenoma (CCA), a relatively rare and poorly understood type of pituitary adenoma with distinct clinical and pathological characteristics. Neuroimaging studies typically describe these neoplasms as large suprasellar masses, often with invasion of the cavernous sinus and adjacent structures. The most common clinical presentation is that of a macroadenoma with invasion into the sphenoid and cavernous sinuses. There is a strong female predominance. Most such tumors are ACTH-secreting adenomas which result in Cushing disease. Patients can also present with symptoms of mass effect (headaches and visual disturbances) caused by endocrinologically silent ACTH-positive adenomas. The patient presented here had no evidence of Cushing disease in the pre- or postoperative periods. CCAs with elevated cortisol levels are much more commonly reported in the literature than those without elevated cortisol levels. Due to their scarcity it is unclear exactly how the functional status of a CCA relates to its clinical course. It remains important for clinicians to be aware of this variant of pituitary adenoma because of its propensity for a more aggressive clinical course.
Crooke hyaline change is a common histologic finding described in nonneoplastic pituitary corticotrophs exposed to persistently elevated cortisol levels. Some corticotroph adenomas show Crooke hyaline change in neoplastic cells, and when more than 50% of adenoma cells exhibit Crooke hyaline change it is known as a CCA. The affected corticotrophs accumulate excessive amounts of cytoplasmic intermediate filaments of cytokeratins along with concomitant displacement and often reduction of cytoplasmic organelles and secretory granules, resulting in a pink hyalinized appearance of the cytoplasm seen on H&E staining of cytologic smears (Image B), frozen sections (Image C), and paraffin sections (Image D). These so-called Crooke cells may have eccentric nuclei pushed to one side by paranuclear collections of displaced normal cellular organelles (Image C, arrow), together encircled by pale hyalinized cytoplasm and often rimmed by amphophilic granular cytoplasm (Image D). The accumulated cytokeratin filaments are best identified as distinct perinuclear rings by IHC for low-molecular-weight cytokeratins such as Cam 5.2 (Image E). Tumor cells in CCA are immunoreactive for ACTH, which decorates peripheral cytoplasm of Crooke cells and negatively highlights non-immunoreactive perinuclear cytokeratin masses (Image F). Although these tumors are clinically aggressive and often invade the cavernous sinuses and nearby structures, they do not display high mitotic activity and MIB-1 (Ki-67) immunolabeling is often very low (Image G).
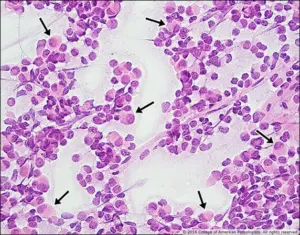
Image B: H&E stain smear, high magnification. |
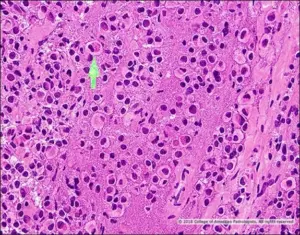
Image C: H&E stain frozen section, high magnification. |
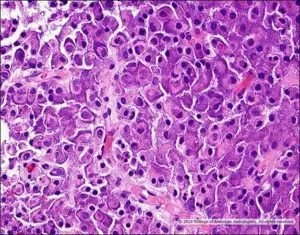
Image D: H&E stain, high magnification. |

Image E: Low-molecular-weight cytokeratin Cam 5.2 IHC stain, high magnification. |
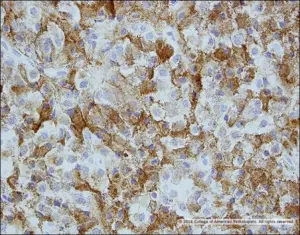
Image F: Adrenocorticotropic hormone (ACTH) IHC stain, high magnification. |

Image G: MIB-1 (Ki-67) IHC stain, intermediate magnification. |
CCAs are rare, clinically aggressive tumors, with fewer than 100 cases reported in the literature so far. Increased frequency of cavernous sinus invasion makes gross total resection difficult, which contributes to the high recurrence rate of 66%. Patients with CCAs have been reported to have persistent/recurrent visual disturbances and elevated ACTH levels despite multiple resections, aggressive medical management, and stereotactic radiosurgery. In cases of recurrent CCA refractory to conventional methods, there are reports of successful use of temozolamide in obtaining radiographic tumor regression and ACTH level reduction.